
Frozen Shoulder: Managing Stiffness Without Forcing Recovery
13
Oct
Frozen Shoulder: Managing Stiffness Without Forcing Recovery
Key Takeaways & Summary
- Shoulder stiffness often becomes obvious during an ordinary task: fastening clothing, reaching a shelf, or turning comfortably in bed.
- Frozen shoulder can involve pain and restricted movement, but other shoulder problems can look similar.
- Consult with the experienced specialists and clinical teams at hnc hospitals for personalized diagnostics and treatment options.
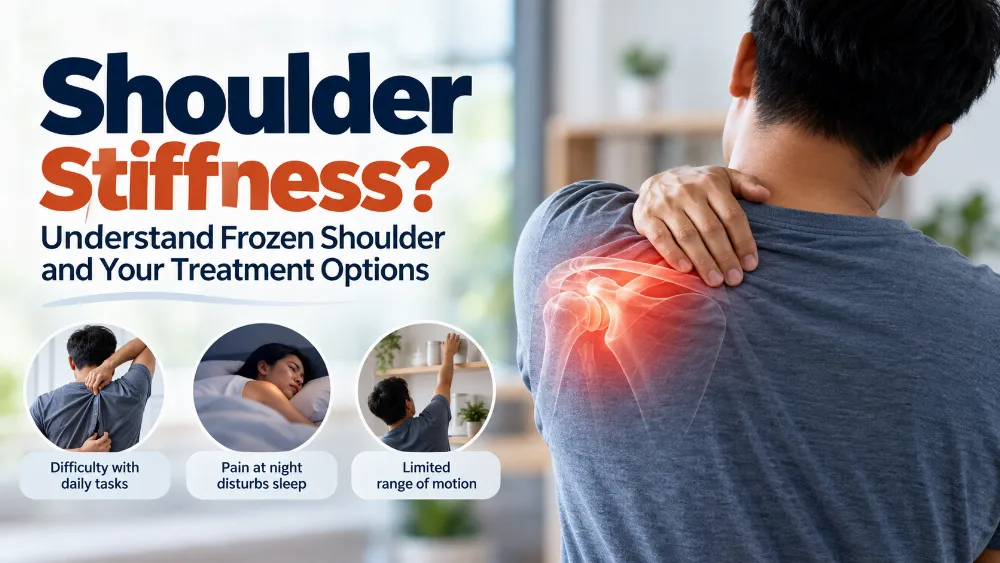
Shoulder stiffness often becomes obvious during an ordinary task: fastening clothing, reaching a shelf, or turning comfortably in bed. Frozen shoulder can involve pain and restricted movement, but other shoulder problems can look similar. Diagnosis matters before you force stretching or buy equipment promising rapid recovery. This article explains how to prepare for assessment, discuss symptom control, and set achievable rehabilitation goals. For people seeking shoulder care in Mattannur and Kannur, the most useful approach connects the diagnosis with sleep, work, and the activities that matter in daily life.
Describe stiffness as well as pain
Tell the clinician which movements have become difficult and whether another person can move the arm farther than you can. Do not test this forcefully at home. Note when symptoms began, any injury, previous surgery, and whether the change developed gradually. Describe pain at rest, during movement, and at night. A list of affected tasks can help convey the problem more clearly than saying the shoulder is frozen. Include whether neck symptoms, tingling, weakness, or pain elsewhere occur. These details help distinguish a stiff shoulder from other causes and guide an appropriate examination.
Check whether urgent assessment is needed
A new major injury, deformity, sudden inability to move the arm, fever with a hot or swollen joint, or severe deterioration requires prompt assessment. Shoulder discomfort with chest pain, breathlessness, sweating, or other signs of acute illness should be treated urgently rather than assumed to be a local joint problem. Seek advice about new significant weakness or neurological symptoms. The term frozen shoulder should not be used to explain every painful arm. If a diagnosis was made earlier, report new symptoms rather than assume they are part of the same condition. Changes can alter the care plan.
Make the examination and investigation plan clear
The clinician will consider movement, pain, the history, and relevant medical conditions. Tell the team about diabetes and any earlier shoulder treatment. Imaging may be advised to answer a particular question, but not every person needs every scan. Ask what supports the diagnosis and whether another cause needs to be excluded. Bring previous reports and any exercise programme already attempted. If you have tried injections or treatment elsewhere, explain when and with what effect. A clear sequence prevents duplicated care and helps the clinician judge whether the present plan needs adjustment.
Work with tolerable rehabilitation goals
Frozen shoulder recovery can take time, and aggressive stretching is not a reliable shortcut. If physiotherapy is recommended, ask for exercises suited to the current symptoms and stage of management. Learn the movements through demonstration and confirm what degree of discomfort is acceptable. Set goals such as improving a dressing task or reaching a particular shelf rather than demanding immediate full movement. Keep a brief record of function and exercise response. If pain consistently worsens or the programme is impossible to follow, contact the therapist for review. A usable plan is more effective than an ambitious routine abandoned after a few days.
Address sleep and the working day
Tell the clinician if night pain is disrupting sleep, because exhaustion can make rehabilitation harder. Discuss comfortable positioning and appropriate symptom control rather than experiment with repeated high doses of pain medicine. Review work tasks that require overhead reaching, carrying, or sustained arm positions. Temporary adjustments may help you remain active while reducing avoidable aggravation. Ask whether a workplace note is appropriate if tasks need changing. At home, move frequently used items within comfortable reach and share difficult chores where possible. These practical changes should support recovery without encouraging complete inactivity or dependence on others for every task.
Discuss treatment choices as decisions
Different options may be considered according to symptoms, diagnosis, and response to earlier care. Ask what each option aims to improve, what the limitations are, and what follow-up is required. If an injection or procedure is proposed, discuss relevant medicines, medical conditions, and preparation instructions. Do not compare yourself with someone who improved after a single intervention; the starting point and condition may have differed. Seek a clear explanation of when the current approach should be reviewed. Treatment should be evaluated through pain, movement, sleep, and function, not only whether the shoulder still feels stiff.
Explain the household tasks behind the symptoms
Make a short list of tasks that have changed: washing hair, fastening clothing, reaching a shelf, carrying a child, or turning in bed. Identify which matter most and which can temporarily be modified. This helps the clinician and physiotherapist set priorities instead of aiming vaguely for a better shoulder. If another person is helping, discuss how support can preserve independence rather than take over every task. Do not repeatedly reach into painful positions just to prove the limitation. One clear description is enough. The practical aim is to make daily life manageable while the shoulder is assessed and treated, with progress linked to specific activities rather than a comparison with someone else's recovery story.
Plan treatment around access and responsibilities
Discuss how often you can attend appointments, whether travel is difficult, and what time is available for home exercises. A plan requiring frequent visits may need adaptation if work or distance creates barriers. Ask which elements need supervision and which can be practised independently after instruction. If an intervention requires transport or temporary help at home, arrange those details before the appointment. Share concerns about cost or time without embarrassment; they affect whether the plan can be followed. Keep one current set of exercise instructions and remove superseded versions from the place you use them. This reduces confusion when treatment evolves over several reviews.
Judge improvement without forcing a deadline
Choose a small number of outcomes such as a more comfortable night, easier dressing, or reaching a familiar surface. Review them over an agreed interval rather than testing the shoulder many times each day. Some changes may be gradual, and a fluctuating day does not necessarily explain the overall course. Report consistent deterioration, new symptoms, or inability to follow the programme. Ask how the team distinguishes expected variability from a need to adjust treatment. A realistic review process can reduce pressure to seek increasingly aggressive stretching or repeated uncoordinated interventions. The focus should remain on safe function and a plan that fits the clinical findings.
If exercise instructions change, ask which earlier movements should continue and which should be replaced. Keep the current programme in one clearly labelled easily accessible place. Mixing several versions can make progress difficult to interpret. At review, describe the actual routine you followed, including breaks caused by pain, work, or travel, so adjustments are based on your experience.
Ask whether the programme needs adapting when work duties or sleep disruption change substantially.
Common questions about frozen shoulder
Should I force the arm through the pain?
Do not force movement as a self-directed strategy. Ask the clinician or physiotherapist to demonstrate an appropriate programme and explain when to stop or seek review.
Is stiffness always frozen shoulder?
No. Other joint, tendon, injury, or neurological problems may affect movement. Assessment is needed before applying a label.
Can recovery be given a fixed deadline?
The course varies. Ask for realistic expectations and review points rather than assume that a short online programme guarantees full recovery.
Arrange shoulder assessment locally
For persistent shoulder stiffness, check the relevant hnc orthopaedic or physiotherapy listings and confirm availability at your preferred location. Bring earlier investigations, a medicine list, and examples of difficult tasks. State if sleep or work is significantly affected. A useful consultation should establish the likely cause, an achievable care plan, and the changes that require earlier contact. Recovery becomes easier to manage when the instructions fit the person's actual responsibilities and progress is reviewed consistently.
Explore hnc departments, check doctor listings, or view appointment information.
Further reading

